



October 30, 2026
A Whole-Systems Approach to Design for Autism
Interior design and architecture often address autism spectrum disorder (ASD) simplistically, assuming people are “hypersensitive” to sensory input, “hyposensitive,” or somewhere in between.
Even well-designed sensory spaces can fail if they ignore individual biology and context. What helps one autistic person may disorient another. In recognition, there are more evidence-based, lived-experience approaches.
A key catalyst in this three-part series is a landmark study by Litman et al. (2025), using SPARK cohort data analyzing 5,000-plus children. The study found autism has four distinct phenotypes, with varying characteristics and patterns.
Applying this scientific insight to design requires a dynamic, multidimensional tool. In response, this article introduces the ASD Design Matrix framework and its core components.
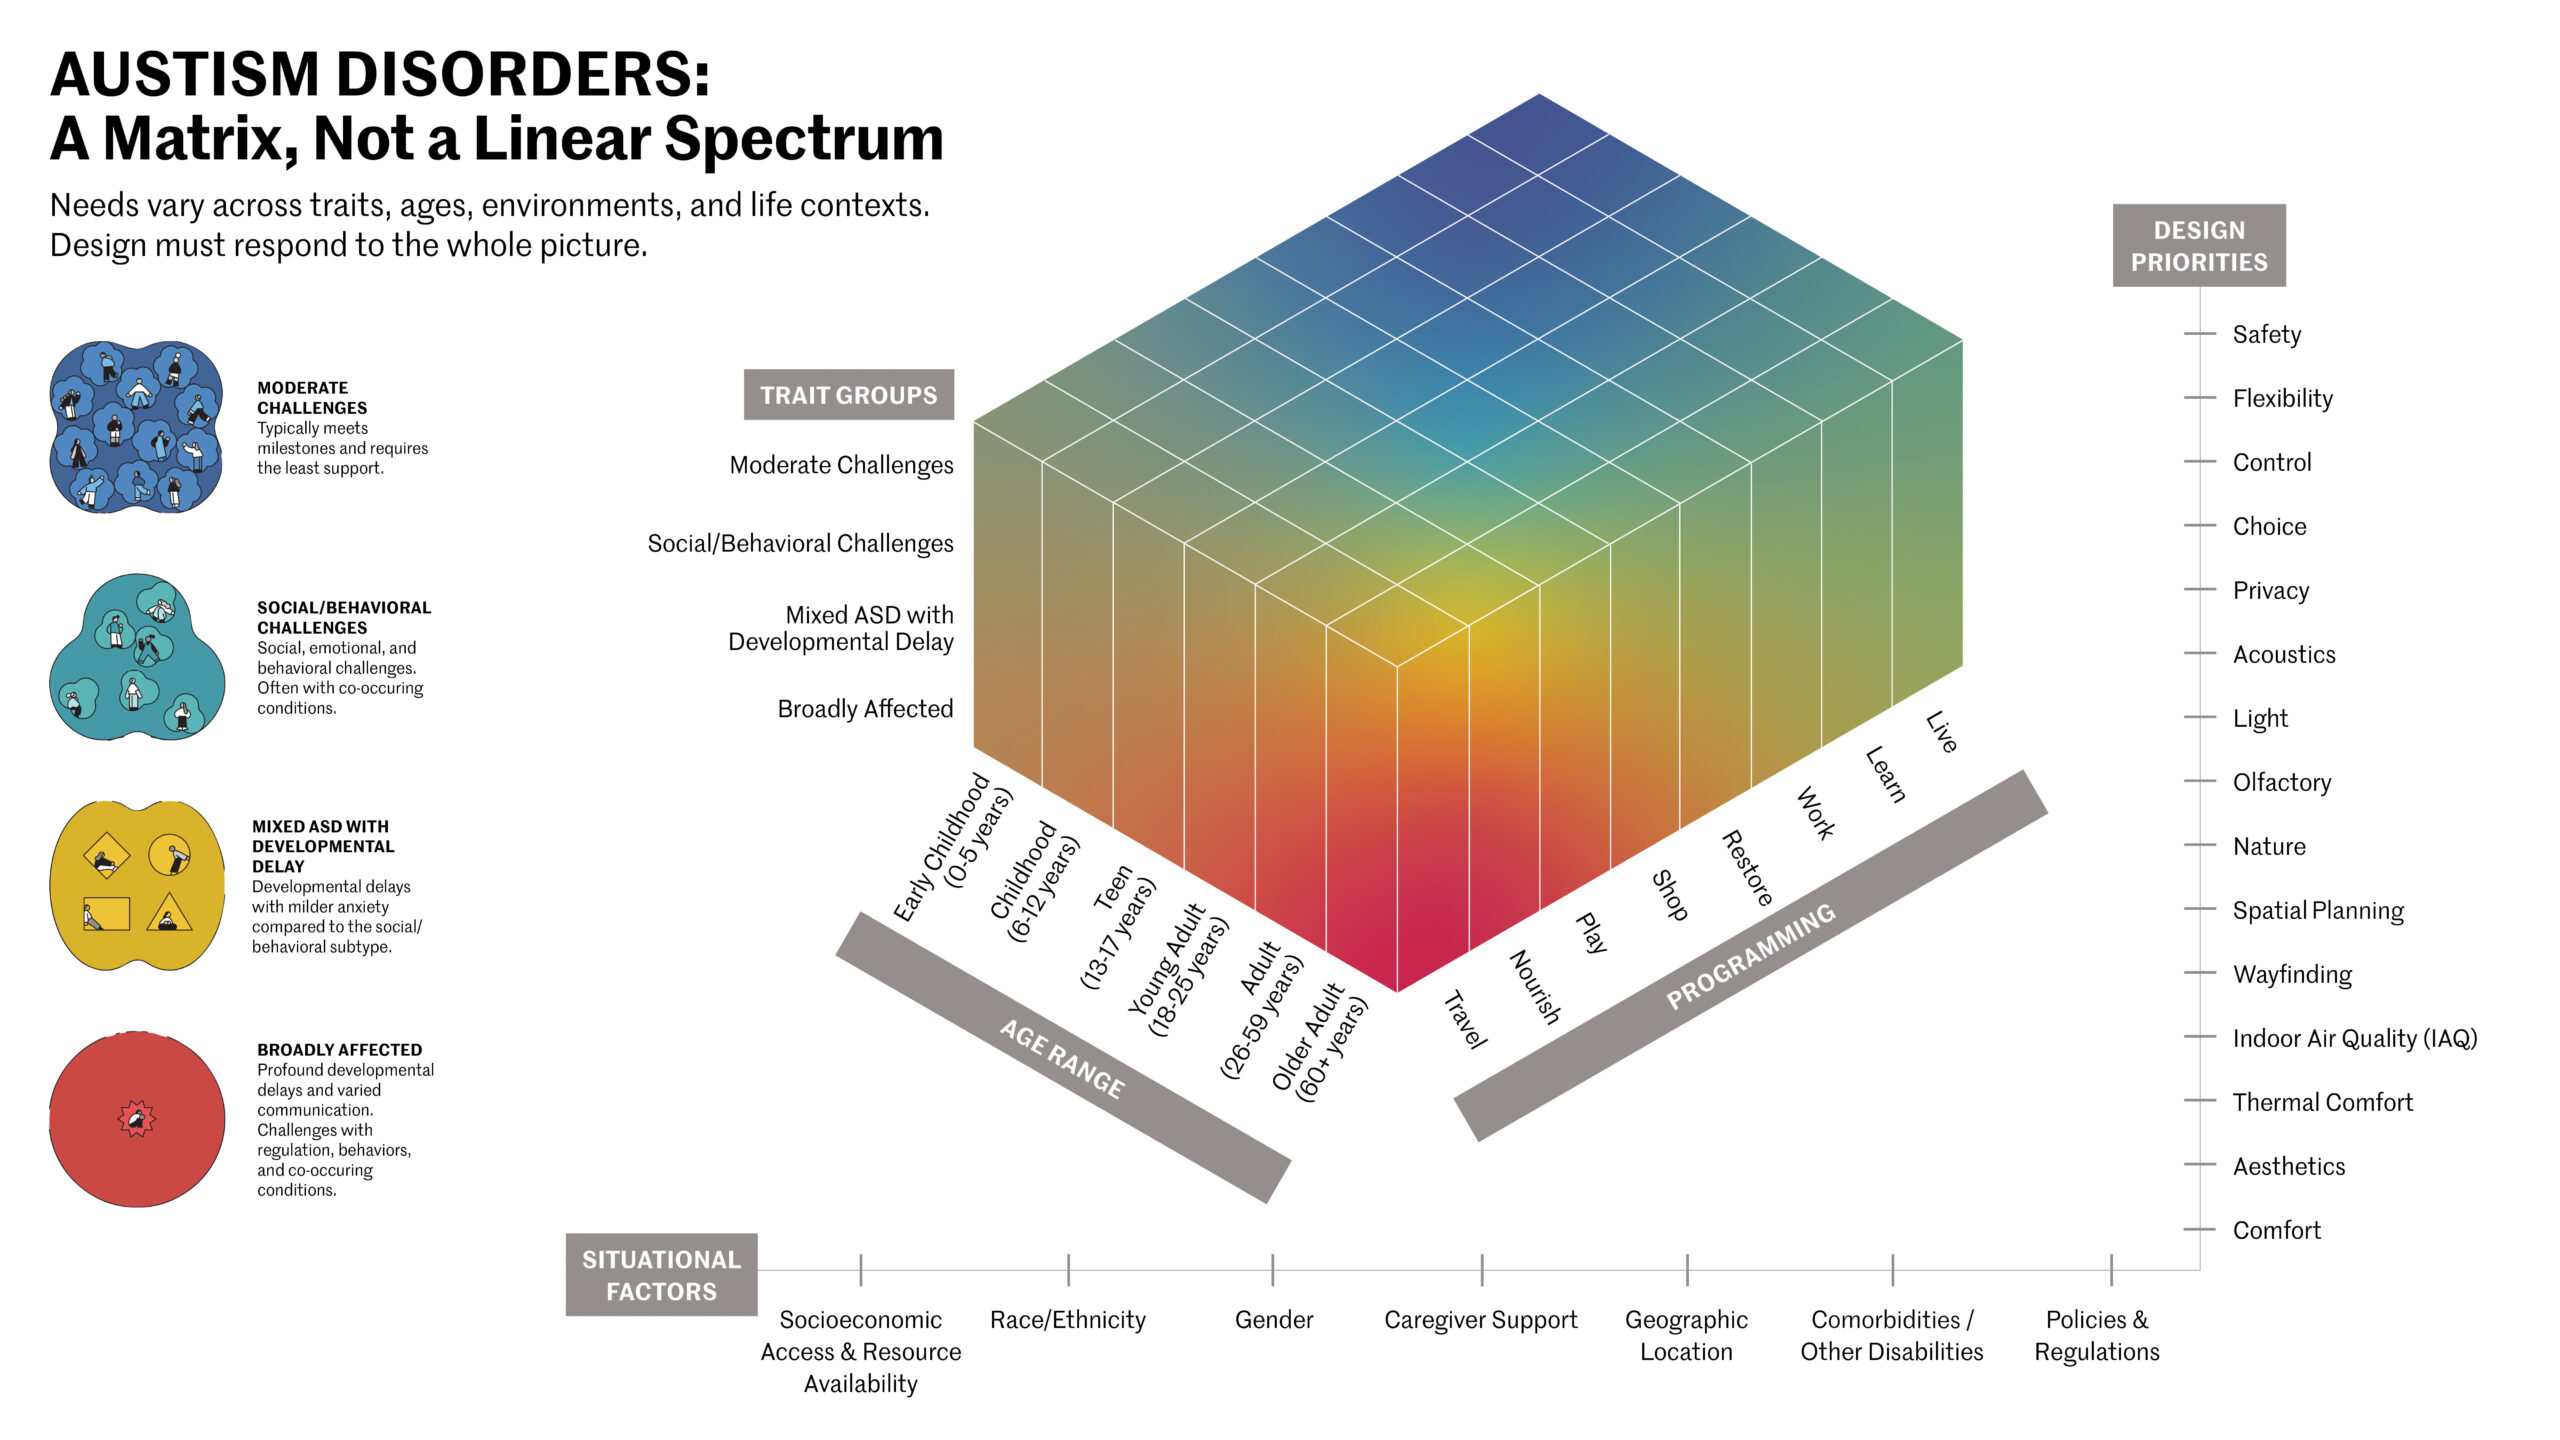
THE ASD DESIGN MATRIX COMPONENTS
Neuroinclusive design requires moving beyond checklists. The ASD Design Matrix organizes existing research by intersecting a person’s trait groups, life stage, environment, and societal factors. The framework centers on five core components:
01. The Person (Trait Groups): Biologically distinct autism subtypes.
02. The Lifespan (Developmental Age): Needs at different life stages.
03. Space Types: Defined by operational rules and context.
04. Design Priorities: Internal physical and sensory realities.
05. Situational Factors: Social and systemic elements affecting care and access.

The Human Dimension
01 The Person (Trait Groups)
The matrix uses four ASD subtypes. Each group has unique patterns. Though some overlap, understanding these patterns helps designers support people with ASD. The trait groups are:
Moderate Challenges: Require the least support; meet typical developmental milestones while qualifying for an ASD diagnosis.
Social/Behavioral Challenges: Exhibit core autism traits such as social challenges, regulation difficulties, and repetitive behaviors. They often have co-occurring conditions, like anxiety, depression, or obsessive compulsive disorder OCD.
Mixed ASD with Developmental Delay: Highest variability; typically show developmental delays (e.g., walking, talking) and milder anxiety than the Social/Behavioral group.
Broadly Affected: Most vulnerable; face profound developmental delays, varied communication, regulation challenges, repetitive behaviors, and co-occurring psychiatric conditions.
02 The Lifespan (Age Range)
Effective design adapts across lifespan and trait groups. Categorizing users by developmental stage clarifies unique needs and cultural impacts.
Early Childhood (0–5 years): Core autism traits often emerge. Early identification and intervention can shape later functioning and participation (CDC, 2026; Autism Action Partnership, n.d.; Wang et al., 2026). Rapid language, play, and social development mean children with ASD may follow different paths. Supportive, low-stress environments and early services are crucial (Lai et al., 2017).
Childhood (6–12 years): Children navigate school, peers, and academic demands. Children with ASD often have differences in social communication and sensory processing (KidsHealth, n.d.; Lai et al., 2017; Wang et al., 2026). Design may support learning, self-esteem, and inclusion (McAllister et al., 2012; Tola et al., 2021; Lai et al., 2017).
Teen (13–17 years): Adolescence brings identity formation, peer relationships, and mental health vulnerability. Teens with ASD may experience increased anxiety, depression, and social stress due to rising expectations for independence (Wang et al., 2026; MacLennan et al., 2023). Supportive environments help positive development (Lai et al., 2017).
Young Adult (18–25 years): Transition to higher education, work, and independent living brings service gaps and new self-advocacy demands (Wang et al., 2026; Lai et al., 2017). Responsive spaces can enable success and support inclusion (Tola et al., 2021; Lai et al., 2017).
Adult (26–59 years): Adults with ASD may face challenges in employment, relationships, and participation, with many reporting unmet needs (Lai et al., 2017; Wang et al., 2026). Inclusive spaces and services support quality of life and autonomy (MacLennan et al., 2023; Lai et al., 2017; Wang et al., 2026).
Older Adult (60+ years): Autism in later life is less studied, but elders with ASD may face challenges from aging, health care access, and isolation (Wang et al., 2026; Lai et al., 2017). Environments should support dignity, connection, and other health challenges (Tola et al., 2021; MacLennan et al., 2023; Lai et al., 2017).
03 Environmental Factors and Space Types
Space types often hold different operational rules, codes, and context. They can exist independently as primary spaces or nested as zones within them. Strategies should be calibrated specifically to:
Live: space that prioritizes daily living activities (e.g., residential, independent care, group home, long-term care, etc.)
Learn: space that prioritizes learning (e.g., schools, work, training facilities, libraries, etc.)
Work: space that prioritizes work activities and productivity (e.g., offices, training centers, labs, retail, warehouse, construction sites, etc.)
Restore: space that prioritizes rest and healing (e.g., hospitals, therapy centers, clinics, schools, religious spaces, workspaces, spas, etc.)
Shop: space that prioritizes sale of goods or services (e.g., stores, shopping centers, warehouses, service centers, etc.)
Play: space that prioritizes recreation or imaginative play (e.g., entertainment facilities, stadiums, parks, playgrounds, gyms, museums, etc.)
Nourish: space that prioritizes preparing, consuming, or storing food or drink (e.g., restaurants, bars, kitchens, pantries, cafeterias, etc.)
Travel: space that prioritizes public tourism (e.g., transit, hotels, resorts, etc.)
04 Design Priorities
Design priorities are the main physical and sensory conditions within a space. Designers must manage environmental factors that support user well-being, health, and safety. While these are important for everyone, specific priorities often exist for people with ASD. These are the elements designers control, shaping the sensory responses that influence how people experience and regulate in a space:
Safety: ensuring psychological and physical protection
Flexibility: enabling modification and adjustment (e.g., furniture, equipment, or physical infrastructure without major demolition)
Control: providing personal ability to guide or manage elements (e.g., operable windows, temperature, light, furniture, etc.)
Choice: the agency to select elements (e.g., variety of equipment, furniture, spaces, or zones)
Privacy: providing visual and physical seclusion
Acoustics: managing noise, sound sensitivity, frequency, and music
Light: regulating daylight, electric light, and glare
Olfactory: controlling odor and smell
Nature: integrating views, access, fractals, and biomorphic shapes and forms
Spatial Planning: organizing sequence, zones, transitions, and compartmentalization
Wayfinding: implementing visual cues, signage, prompts, and maps
Indoor Air Quality (IAQ): filtering allergens and pollutants (e.g., volatile organic compounds, particulate matter, and carbon monoxide)
Thermal Comfort: regulating temperature, velocity, and humidity
Aesthetics: selecting color, pattern, texture, and imagery
Comfort: managing furnishings, equipment, cleanliness, and clutter
Social Determinants
05 Situational Factors
These social elements are often beyond a designer’s control and embedded in larger systems. When marginalized identities intersect, access and care barriers increase (Absoud, 2022; Kuo et al., 2022; Malik-Soni et al., 2022). The following factors should be considered:
Socioeconomic Access & Resources: Not all families or facilities have access to optimal interventions or resources. Design solutions should be scalable to support various socioeconomic levels for needed support (Lai et al., 2017).
Race/Ethnicity: Cultural background shapes how spaces and behaviors are understood, influencing perception (Akankwatsa et al., 2025; Jonauskaite et al., 2020). Black and Hispanic children with ASD are diagnosed later, partly because provider bias affects equitable care (Constantino et al., 2020). Chronic racialized stress further compounds disadvantage for Black individuals (Geronimus, 1992; Forde et al., 2019).
Gender: Girls and women are often underdiagnosed, partly due to camouflaging (Hull et al., 2020), which is linked to anxiety, depression, and exhaustion (Cook et al., 2021). In addition, transgender, nonbinary, and gender-nonconforming individuals show higher autism rates (Warrier et al., 2020). Male-centric clinical models contribute to late or missed diagnoses for these groups, affecting care and accommodation (Green et al., 2025; Lonergan, 2021; Peña-Casquero et al., 2026).
Caregiver Support: Caregivers of autistic children experience greater psychological, physical, and mortality health risks than other caregivers (Dijkstra-de Neijs et al., 2020; Dückert et al., 2025; Ogba et al., 2020). Supporting caregivers is essential, as the health and well-being of individuals with ASD often depend on the quality of their care.
Geographic Location: Zip code is a key determinant of health and access (Vo et al., 2023). Nearly 84% of U.S. counties lack autism diagnostic resources (Ning et al., 2019). Rural families face long travel, provider shortages, and limited access to trained clinicians (Vanegas et al., 2023).
Comorbidities: Illness, disease, and disability often compound autism (Khachadourian et al., 2023). About 74% of people with ASD have a co-occurring condition (Khachadourian et al., 2023), which can affect tolerance of environments (Lai et al., 2023). Spaces designed only for “autism” may fail those with multiple conditions (Khachadourian et al., 2023).
Policies and Regulations: Policies influence how people use and access supports. Workplace accommodations are requested more often when perceived control and support are coupled with policies (Dong et al., 2023). Employees with ASD are more likely to use accommodations when disclosure feels low risk (Romualdez et al., 2021).
Conclusion
By integrating these elements, the ASD Design Matrix drives integrated design. It offers a road map reflecting human diversity, shifting from reactive to proactive whole-systems guidance. Successful environments go beyond sensory management and are systemically designed for user diversity. Because ASD is complex and needs vary, involving experts in ASD and neurocognition is crucial throughout the design process.
The final article in this series shifts from theory to practice, demonstrating the ASD Design Matrix with research-based personae and case studies, offering recommendations to help practitioners advance ASD design.
Angelita Scott, PhD, is the founder of Culturwell, a consultancy focused on well-being and belonging through design research, strategy, and education for the built environment. She was the lead author of the IWBI WELL Equity Rating, which includes the first evidence-based neurodiversity design features in a U.S. building standard or rating.
Would you like to comment on this article? Send your thoughts to: [email protected]
Latest

Profiles
Young Projects Designs for the Unknown
The Brooklyn studio experiments with materials, fabrication, and form to create architecture that puts discovery at the forefront.

Viewpoints
The Biomimicry Institute Launches a Nature-Positive Alliance
Early adopters like COOKFOX, Mithun, HKS and others pledge to emphasize ecological performance in the built environment.